
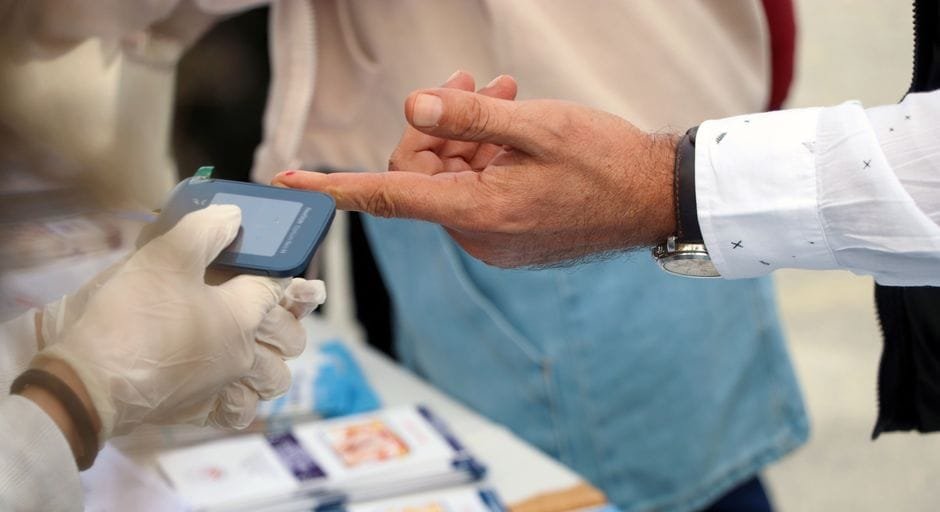
Sarcopenia — the age-related loss of muscle mass and strength — isn’t one condition with one risk profile. A new study of frail older adults with diabetes found distinct patterns within it, and the patterns differed in the complications people already had.[1]
Two versions of the same diagnosis
Researchers studied 109 adults aged 70 and older who were living with both diabetes and frailty. Using standard diagnostic criteria (the European Working Group on Sarcopenia in Older People, or EWGSOP2), they found sarcopenia in nearly 79% of participants — and then split those cases into phenotypes based on body composition: how much muscle versus fat each person carried.
The study described three body-composition phenotypes among 107 participants (two people from a very small subgroup were excluded). Two of the patterns stood out, and the abstract does not say exactly which groups each was compared against. Sarcopenic obesity — low muscle mass combined with high body fat — clustered with classic insulin-resistance markers: more central (abdominal) fat, higher triglycerides, a higher triglyceride-glucose index (a marker of insulin resistance), universal metabolic syndrome, and greater insulin dosing needs. Sarcopenia without excess adiposity — low muscle mass without the extra fat — looked different: more nerve damage (neuropathy), more kidney involvement (albuminuria), more cerebrovascular disease, and worse continuous glucose monitor (CGM) readings, despite having similar average blood sugar (HbA1c) numbers to the other group.
That last point is the one worth sitting with: in this study, the group with sarcopenia but without excess body fat had a similar average HbA1c to the other group, yet spent less time in the target glucose range on continuous monitoring and had more existing complications.
What the data can (and can’t) tell us
This was a cross-sectional study of 109 people at one point in time — a real, useful signal, not a definitive map. In the researchers’ own statistical modeling, HbA1c itself was the only factor that independently predicted poor glucose control (time in target range below 70%); phenotype alone didn’t reach statistical significance once other factors were accounted for. The authors are explicit that these are preliminary findings needing confirmation in larger, longer studies. What’s genuinely new here is the descriptive picture: sarcopenia in diabetes isn’t a single entity, and the group with sarcopenia but without excess body fat showed a different pattern of existing complications from the sarcopenic obesity group.
What this means for you
If you or someone you’re caring for is older, living with diabetes, and noticeably losing strength or muscle:
- Ask whether HbA1c tells the whole story. One group in this study had lower time in range despite similar HbA1c, and the authors suggest a continuous glucose monitor may add information. Their adjusted model still found HbA1c was the only independent predictor of poor time in range, and they say the findings need confirming before they change management, so treat CGM as a question for your care team.
- Track body composition, not just weight or BMI. Weight or BMI alone can’t show how much of the body is muscle. In this study, low muscle mass without excess body fat was linked to its own pattern of existing complications, including nerve and vascular ones.
- Bring muscle mass into diabetes management conversations. Ask your care team whether a body composition assessment (even a simple bioelectrical impedance scale) makes sense alongside routine diabetes monitoring, especially if strength or mobility has changed recently.
Please don’t change your insulin or other diabetes medication on your own because of a body-composition label. Any change should come from your care team.
Diabetes and muscle loss are frequently managed as separate problems. This study is a reminder that in older adults, they’re often the same problem wearing different faces.
References
- Guevara E, Simó-Servat A, Perea V, et al. “Body composition-defined sarcopenia phenotypes, diabetes complications, and CGM-derived glycemic profiles in frail older adults with diabetes: a cross-sectional study.” The Journal of Nutrition, Health & Aging, 2026;30(10):100947. Finding used: among 109 adults aged 70+ with diabetes and frailty, sarcopenic obesity clustered with insulin-resistance markers (central adiposity, higher triglycerides, universal metabolic syndrome), while sarcopenia without adiposity clustered with more neuropathy, albuminuria, cerebrovascular disease, and lower CGM time-in-range despite similar HbA1c; HbA1c, not phenotype, was the only independent correlate of poor glycemic control in adjusted models. DOI: 10.1016/j.jnha.2026.100947. Source: PubMed 42570512. ↑︎

Kurt Greiner
Kurt is a digital strategist and IT professional blending emerging technology with practical application to help businesses and individuals streamline their digital presence. His current work focuses on the intersection of intentional living and technological resilience, exploring how individuals can leverage modern tools to navigate the second half of life with purpose.
Leave a Reply